Ask questions across claims linked to experiments, exact results, limitations, and sources.Know what the science actually supports before you trust the answer.
Press Enter ↵ to search evidence
Explore by Goal
"Nothing in life is to be feared, it is only to be understood. Now is the time to understand more, so that we may fear less."
- Marie Curie
Quick Answer
Copied
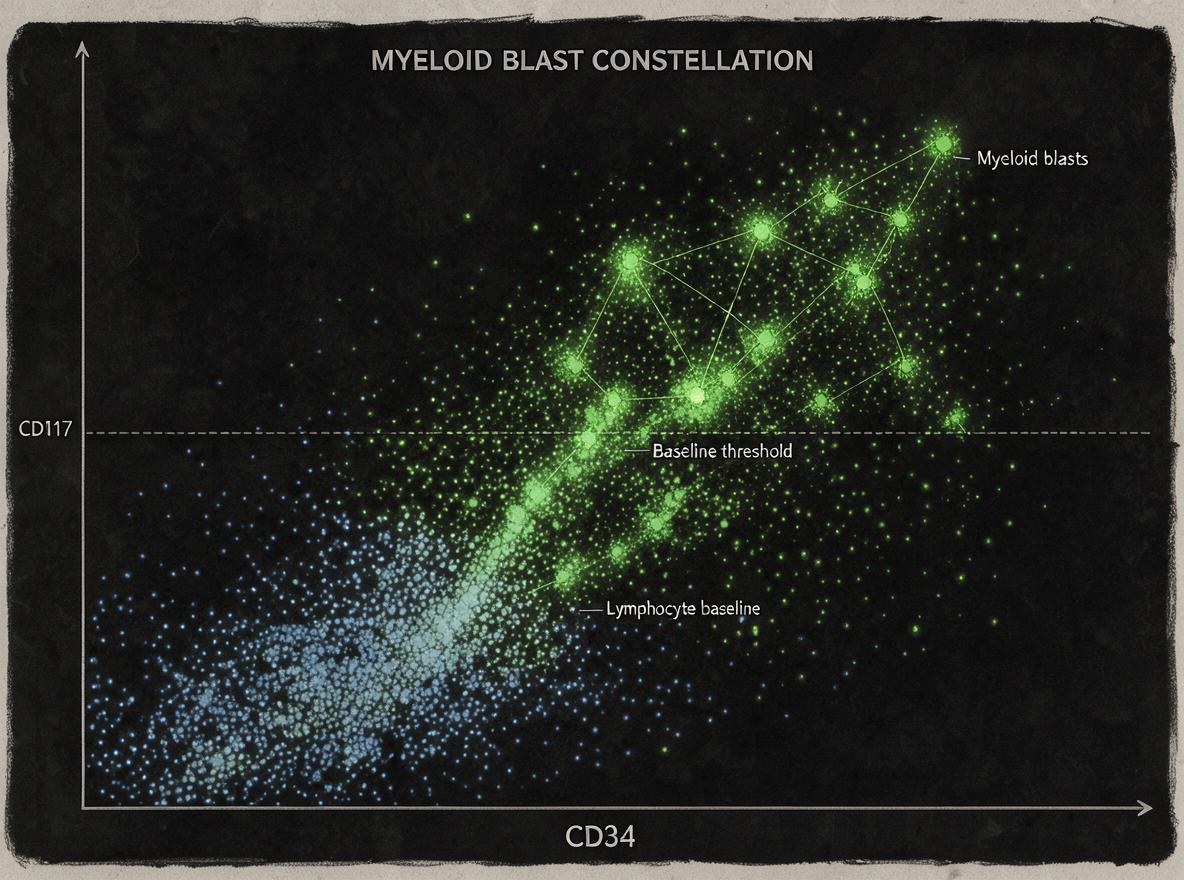
Bras et al. define flow-cytometric MPO positivity as ≥20% of acute leukaemia cells exceeding a lymphocyte-based threshold (780 FIU) on the EuroFlow ALOT, validated in 1,734 multicentre cases (98.9–99.2% of ALL MPO-negative; ~30–33% of AML MPO-negative). The main weakness is the absence of a cytomorphological gold-standard reference, acknowledged by the authors.
Long Answer
What the paper establishes
The study closes a real diagnostic gap: despite flow cytometry's advantages for MPO lineage assignment, no de facto standard definition of MPO positivity existed. Using the standardised EuroFlow Acute Leukaemia Orientation Tube (MPO:FITC, clone MPO-7) and 1,734 AL cases, the authors systematically optimised both the positivity threshold (780 FIU, lymphocyte-based) and the positivity cut-off (≥20% of AL cells), achieving near-optimal AUCs for both ALL-vs-monocyte (0.993) and WHO-NEG-vs-WHO-POS AML (0.946) discrimination.
Cohort composition and validation design
The training cohort (DCOG 2010–2015; Erasmus MC 2010–2018: 527 BCP-ALL, 134 T-ALL, 519 AML) and independent five-centre validation cohort (315 BCP-ALL, 56 T-ALL, 154 AML, 29 MPAL) showed near-identical results, supporting assay stability over time, across centres and across two cytometrists.
Critical appraisal
Reference standard gap: Cytomorphological MPO status was not used as ground truth, so the definition is internally optimised against control pairs (ALL vs monocytes; WHO-NEG vs WHO-POS AML) rather than externally validated against an independent gold standard — a limitation the authors openly discuss.
Circular control selection: WHO-NEG/WHO-POS pairs were not fully MPO-negative/positive (two MPO-positive acute megakaryocytic cases), though temporary exclusion barely changed thresholds — reported robustness evidence.
Conflict of interest: Five authors hold EuroFlow patents licensed to Cytognos and BD Biosciences with royalty payments — a structural incentive favouring the EuroFlow ALOT platform that readers should weigh when assessing the claim that the approach is the missing standard.
MPAL reclassification: Six of 29 MPAL cases became MPO-negative under the new definition and were formally reclassified per WHO criteria — clinically consequential, showing the definition changes diagnoses, not just labels.
Information loss: The binary classifier discards continuous MPO.PPC data; the authors rightly recommend reporting both.
Overall: a methodologically careful, transparently confessional standardisation study of immediate practical utility for AL diagnostics, whose generality beyond EuroFlow-standardised platforms remains asserted rather than demonstrated. What would change this verdict: an independent multicentre comparison against cytomorphological reference MPO status showing superior or equivalent misclassification rates.
Feedback:
Updated: November 13, 2026
BGPT Paper Review
Study Novelty
70%
First de facto standard definition of MPO positivity for the EuroFlow ALOT; prior studies (e.g. 10–13% cut-offs) were smaller and non-standardised, but the concept of MPO flow cytometry thresholds is not new.
Scientific Quality
80%
Large multicentre cohort, stability checks, continuous threshold evaluation, and transparent limitation discussion; main weaknesses are absent cytomorphological reference, imperfect control purity, and disclosed patent/royalty conflicts for five authors.
Study Generality
80%
MPO positivity definition directly affects WHO lineage assignment and MPAL classification in acute leukaemia broadly, though the specific 780 FIU value is platform/protocol-dependent.
Study Usefulness
90%
Provides an immediately adoptable, reproducible MPO positivity rule that completes the ALOT as a fully standardised MPO status assay, with direct clinical classification impact (six MPAL reclassifications).
Study Reproducibility
80%
EuroFlow protocols are publicly available, thresholds/cut-offs fully specified, stability data in supplementary material; but data and software sharing is not explicitly stated.
Explanatory Depth
70%
Deep empirical characterisation of MPO expression heterogeneity (skewness ~76%, subclones ~5%) and information loss from binarisation, though no mechanistic account of MPO-positive ALL biology.
Simulating expected MPO.PPC distributions for ALL and AML cohorts from reported percentages, and Monte Carlo estimating misclassification risk when the 780 FIU threshold varies ±20%.
Get emailed when your analysis is done!
We'll email you the results when your analysis is finished.
Hypothesis Graveyard
Fixed absolute FIU thresholds (e.g. optimised 674/943 FIU) as the best MPO classifier: falsified because they underperformed the lymphocyte-referenced percentage-of-positive-cells statistic across both control pairs.
Cytomorphology as the reference standard for MPO: rejected due to reported inter-expert variability and poor correlation with flow cytometry, undermining its use to validate any flow-based cut-off.

 Explore by Goal
 Quick Answer
 Long Answer
 Top Data Sources
 Ask a Follow-Up
 Key Insight
 Keep Exploring
 Analysis
 Hypothesis Graveyard
 Potential Experiments
 Discussion
