Check whether claims match experiments, exact reported results, and stated limitations.Know what the science actually supports before you trust the answer.
Press Enter ↵ to review paper
Explore by Goal
"Science knows no country, because knowledge belongs to humanity, and is the torch which illuminates the world."
- Louis Pasteur
Quick Explanation
Copied
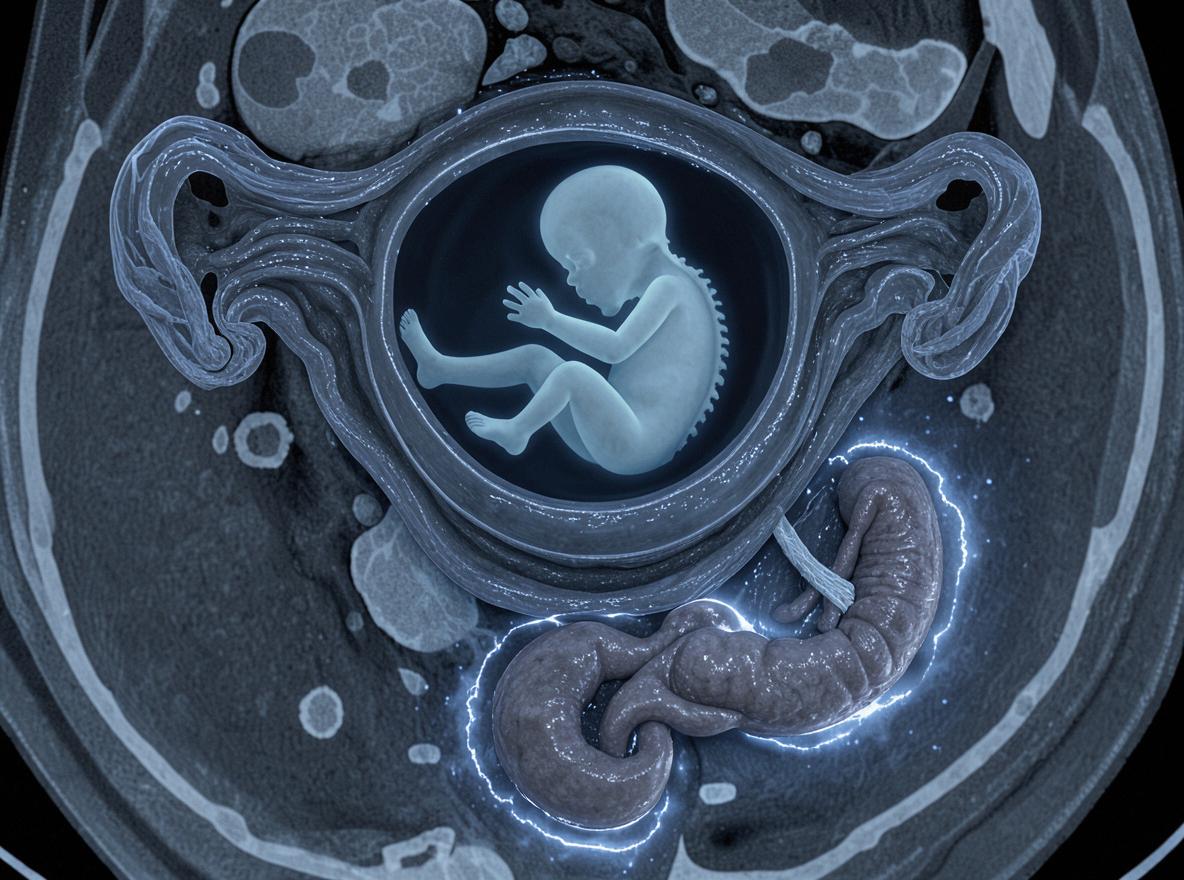
This 2004 single-case report (Aouthmany & Horattas, Dis Colon Rectum) documents the first published ileal pouch perforation during pregnancy: a 30-year-old at 27 weeks with prior IPAA developed a 3-mm J-pouch perforation adherent to the posterior uterus, managed by emergency cesarean with a viable infant and uncomplicated pouch repair. Its value is as a sentinel awareness signal, not evidence of incidence or mechanism.
Long Explanation
Case Substance
A 30-year-old multigravida admitted for preterm labor at 27 weeks (prior IPAA for ulcerative colitis, previous cesarean at 28 weeks) acutely developed generalized abdominal pain and dyspnea 48 hours after magnesium sulfate tocolysis. Vital signs were near-normal (temp 36.2°C, HR 94, BP 112/60) and labs showed only mild leukocytosis (WBC 12,000/mm³, 11% bands) — a reminder that physiologic pregnancy and immunomodulation blunt classic peritonitis signs. A spiral chest CT for suspected pulmonary embolus incidentally revealed free intra-abdominal air. Emergency cesarean yielded a viable infant; a 3-mm perforation at the J-limb tip, adherent to the posterior uterus, was repaired primarily without diversion. Discharge occurred at postoperative day 4. The authors explicitly state this is the first reported case of pouch perforation in pregnancy
Mechanistic Claim — Plausible but Untested
The authors propose adhesions between the enlarged, contracting uterus and the pouch caused the perforation, noting the perforation occurred in the second pregnancy but not the first — an unexplained inconsistency they honestly flag. The prior IPAA literature cited (traumatic, volvulus-associated, and Salmonella-related perforations) supports perforation as a recognized late complication, but the adhesion-tension mechanism in this case is a post-hoc inference from intraoperative findings, not a demonstrated causal chain . A related systematic review of IBD surgery outcomes confirms passive smokers with UC show higher pouchitis rates after pouch surgery, illustrating that pouch complication risk factors are multifactorial and poorly characterized
Critical Limitations
Single-patient design precludes incidence estimation; publication bias likely inflates perceived case uniqueness; no long-term maternal or infant follow-up; no comparison of diagnostic pathways (CT radiation exposure in pregnancy is briefly navigated but not analyzed); and the causal adhesion hypothesis cannot be falsified from one case. The four management guidelines offered (suspicion index, early imaging, broad-spectrum antibiotics, prompt surgery) are expert opinion without evidence grading.
Feedback:
Updated: October 28, 2026
BGPT Paper Review
Study Novelty
70%
First-ever reported case of ileal pouch perforation in pregnancy (2004); clinically novel at publication, though mechanistically an extension of known adhesion-related perforation biology.
Scientific Quality
60%
Clear clinical documentation with quantitative labs, imaging, and operative findings, but zero statistical analysis, no follow-up data, ungraded expert-opinion guidelines, and honest acknowledgment of an unexplained inconsistency (why only the second pregnancy).
Study Generality
40%
Applies to a very narrow population (pregnant IPAA patients), though the diagnostic-delay principle in pregnancy transfers to broader surgical contexts.
Study Usefulness
60%
High differential-diagnosis utility for the rare intersection of IPAA and pregnancy; triggered later awareness in obstetric and colorectal literature despite weak evidentiary weight.
Study Reproducibility
30%
Case reports are inherently non-reproducible; no dataset, no protocol, no incidence denominator.
Explanatory Depth
40%
Mechanism is a plausible single-observation inference (adhesion tension during contractions) without histology, biomechanical analysis, or comparison to non-pregnant adhesion cases.
We'll email you the results when your analysis is finished.
Hypothesis Graveyard
Spontaneous pouch ischemia from gravid compression alone: rejected because the perforation was at the adhesion site with an otherwise viable pouch, and the 3-mm hole morphology matches traction rather than ischemic necrosis.

 Explore by Goal
 Quick Explanation
 Long Explanation
 Top Data Sources
 Ask a Follow-Up
 Key Insight
 Keep Exploring
 Hypothesis Graveyard
 Potential Experiments
 Discussion
