Check a paper's claims against linked experiments, exact results, stated scope, and limitations.Know what falsifiable science actually supports before you trust the answer.
Press Enter ↵ to search evidence
Explore by Goal
"Biology is the study of complicated things that have the appearance of having been designed with a purpose."
- Richard Dawkins
Quick Explanation
Copied
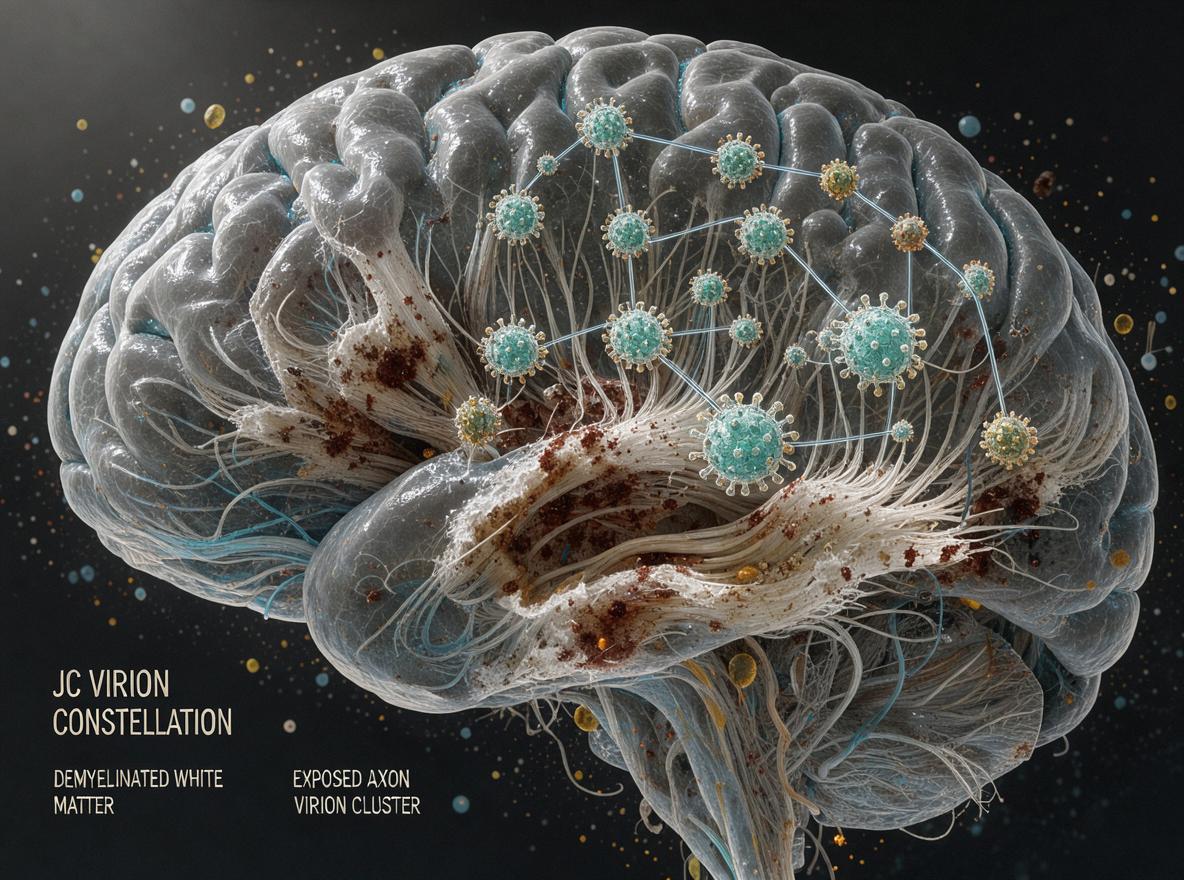
This is a single-patient case report (Frontiers in Immunology, Oct 2024) describing PML co-occurring with neurosarcoidosis in a 65-year-old woman; the authors argue early brain biopsy enabled JCV diagnosis before immunosuppression was escalated, and appropriate PML therapy yielded a favorable outcome. The clinical message is plausible but rests on n=1, with no controlled comparison, so causality between early biopsy and prognosis cannot be established.
Long Explanation
Case Evidence and Clinical Course
The paper reports a 65-year-old woman with prior breast and renal cancer and biopsy-proven cutaneous, ocular, and pulmonary sarcoidosis who was not receiving immunosuppressive therapy due to low disease activity. She presented with progressive speech, reading, and writing difficulties; MRI showed a DWI/FLAIR-hyperintense left temporo-occipital white matter lesion that enlarged over weeks. Admission labs showed elevated sIL-2R (2350 U/mL) and ACE (45.8 U/L); CSF showed elevated protein (59 mg/dL), β2-microglobulin (5.51 mg/mL), sIL-2R (195 U/mL), and a CD4/8 ratio of 10.4, with positive oligoclonal bands. These markers were interpreted as consistent with neurosarcoidosis activity, while cultures were negative for bacterial and acid-fast organisms. The paper's central claim is that because PML was plausible in a progressively worsening parenchymal lesion, an early brain biopsy was performed, enabling histopathologic diagnosis of PML (JCV-associated demyelination) before any escalation of immunosuppressive therapy for presumed sarcoidosis, and targeted PML therapy then produced a favorable prognosis .
Critical Appraisal
Reported observations vs. author interpretations: The biopsy findings and lab values are direct observations; the inference that early biopsy caused the favorable prognosis is an author interpretation that a single case cannot test. Limitations and blind spots: (1) n=1 with no control arm; PML survival is highly variable, and isolated non-HIV PML cases can improve spontaneously. (2) The exact "appropriate therapy" regimen is not fully specified in the available text, limiting reproducibility. (3) The T-cell/sarcoidosis immune milieu could itself have modified PML severity; the paper does not disentangle this confounder. (4) Retrospective narrative timing (symptoms in November/January, referral Day 1 in February) leaves the actual biopsy-to-outcome interval uncertain. (5) Prior malignancies add immunologic context not discussed in depth. Confidence in the descriptive findings is moderate; confidence in the causal claim is low.
The broader clinical lesson—consider PML and biopsy early in progressive white-matter lesions of sarcoidosis patients before escalating immunosuppression—is biologically coherent and aligns with the known risk of PML under immunosuppression, but it should be regarded as a hypothesis-generating observation, not evidence-level guidance.
Feedback:
Updated: November 03, 2026
BGPT Paper Review
Study Novelty
50%
PML in neurosarcoidosis is described as extremely rare, so the case adds novelty; however, PML with sarcoidosis and case-report literature on biopsy-driven diagnosis already exist, limiting novelty to the specific co-occurrence.
Scientific Quality
50%
Careful documentation of labs, imaging, and pathology from a specialized center; but as a case report it is inherently low-level evidence, vulnerable to post hoc narrative bias, and cannot test the causal claim that early biopsy improved prognosis.
Study Generality
40%
Highly specific single-patient scenario; the transferable general lesson (biopsy progressive white-matter lesions before immunosuppression) is broad but not derived from controlled data.
Study Usefulness
50%
Practically useful as a diagnostic caution for clinicians managing sarcoidosis with new CNS lesions, but usefulness is capped by n=1 and unspecified therapy details.
Study Reproducibility
40%
Lab values and imaging findings are well reported, but the therapeutic regimen and timeline details needed to reproduce the management pathway are incompletely specified in the available text.
Explanatory Depth
40%
Provides a plausible clinical-reasoning narrative but no mechanistic insight into why PML arose in non-immunosuppressed sarcoidosis or how the immune milieu shaped outcomes.
We'll email you the results when your analysis is finished.
Hypothesis Graveyard
"Sarcoidosis itself directly caused the white-matter lesion" — rejected because biopsy identified PML pathology, showing the lesion was viral, not sarcoid granulomatous tissue.
"The favorable outcome was due to sarcoidosis-directed immunosuppression" — rejected because the authors explicitly avoided immunosuppressive escalation after identifying PML; immunosuppression would plausibly have worsened it.

 Explore by Goal
 Quick Explanation
 Long Explanation
 Top Data Sources
 Ask a Follow-Up
 Key Insight
 Keep Exploring
 Hypothesis Graveyard
 Potential Experiments
 Discussion
