Analyze how experimental results and claims are presented, scoped, and limited in a paper.Know what the science actually supports before you trust the answer.
Press Enter ↵ to analyze
Explore by Goal
"Biology is a science of three dimensions. The first is the study of each species across all levels of biological organization, molecule to cell to organism to population to ecosystem. The second dimension is the diversity of all species in the biosphere. The third dimension is the history of each species in turn, comprising both its genetic evolution and the environmental change that drove the evolution."
- E. O. Wilson
Quick Explanation
Copied
This 2009 Critical Care Medicine narrative review by Sharshar and colleagues remains a foundational, well-cited synthesis of sepsis-associated encephalopathy (SAE) pathophysiology, diagnosis, and differential diagnosis, correctly emphasizing that SAE is a diagnosis of exclusion requiring systematic workup. Its core claims—multifactorial mechanisms (BBB breakdown, neuroinflammation, oxidative stress) and no SAE-specific therapy—have been substantially reinforced but also refined by subsequent biomarker meta-analyses and multi-omics work .
Long Explanation
Core Content and Enduring Value
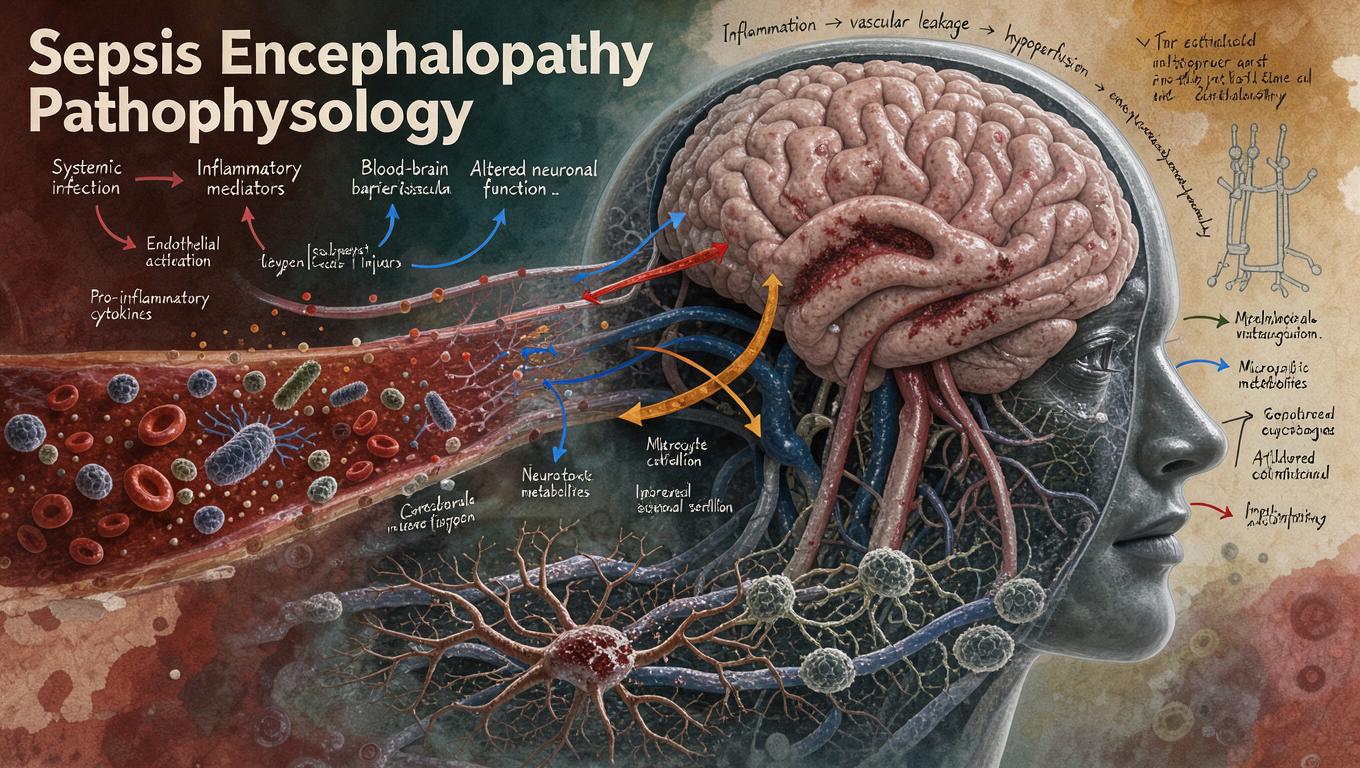
This 2009 narrative review in Critical Care Medicine (Sharshar et al., 60 references) remains one of the most-cited foundational texts on sepsis-associated encephalopathy, later cited by major updates in Nature Reviews Neurology and Expert Review of Anti-Infective Therapy . The review's central structure—(1) SAE as diffuse brain dysfunction without direct CNS infection, distinct from septic encephalitis; (2) multifactorial pathophysiology spanning vagal/circumventricular brain signaling, endothelial activation, BBB breakdown, neurotransmitter disruption, mitochondrial dysfunction, oxidative stress, and apoptosis; (3) a systematic diagnostic algorithm; and (4) an explicit differential diagnosis list—was prescient and remains the backbone of modern frameworks that now add septic-embolic and septic-metastatic encephalitis as a continuum .
Figure (reported data): The review's quantitative anchor is that EEG mortality ranged from 0% with normal EEG to 67% with burst suppression, and GCS <8 raised mortality to ~63%—both drawn from cited primary studies, not new data . Intermediate EEG grades were not quantified in the source, which the figure makes explicit.
What Subsequent Evidence Confirms—and Refines
The review's biomarker skepticism (NSE, S100β "not correlated with clinical or EEG severity") proved partly prescient but requires updating. Two later meta-analyses found NSE significantly higher in SAE vs non-encephalopathic sepsis (MD 12.39 µg/L, 95% CI 8.27–16.50; MD 6.82, 95% CI 5.43–8.21), yet with extreme heterogeneity (I² 98.9–99.9%) and small-study effects (Egger P=0.020), consistent with the review's caution . A 2026 Bayesian network meta-analysis (16 studies, n=1,666) extended the panel—TRAF6 and S100A8 ranked highest but on single-study evidence—confirming that the review's 2009 caution about biomarker readiness still applies .
Critical Limitations and Blind Spots
Confirmed blind spot the paper itself acknowledged only partially: the review notes "long-term cognitive and psychological sequelae of SAE are unknown" in a truncated sentence, and later work showed this is a major gap—many survivors develop long-term cognitive deficits, and the delirium-to-dementia question remains open . Structural limitations: as a narrative review it has no systematic search strategy, no evidence-quality appraisal, and conflates animal-model findings (rat LPS/CLP oxidative stress, apoptosis) with human evidence without weighting translational uncertainty—a concern later reviews flag explicitly . The therapeutic section's speculation on insulin, activated protein C, and steroids was appropriately flagged as unproven and has remained so. The stated prevalence framing ("about a third of septic patients had GCS <12") reflects 1996-era data; modern estimates range 8–70% depending on definitions, underscoring definitional instability the review partially acknowledged .
Verdict
A high-quality, influential synthesis whose diagnostic algorithm and mechanistic framing aged well; its main weaknesses are narrative-method opacity, unweighted animal-to-human extrapolation, and pre-biomarker-era data now superseded by quantitative syntheses. Confidence: moderate-to-high for the diagnostic/differential content (consistent across independent later reviews), lower for pathophysiologic causal claims (largely preclinical).
Feedback:
Updated: November 02, 2026
BGPT Paper Review
Study Novelty
60%
For 2009, consolidating SAE mechanisms and an explicit differential-diagnosis algorithm was a meaningful but not groundbreaking contribution; the framework built on the authors' own prior neuropathology and delirium work rather than introducing fundamentally new concepts.
Scientific Quality
70%
Well-organized, mechanistically rich, and transparent about uncertainty (e.g., controversial cerebral blood flow data, unproven therapies). Weaknesses: narrative method without systematic search, no evidence grading, animal-model findings presented alongside human data without translation weighting, and minor typographical/citation-format errors in the source text.
Study Generality
70%
SAE principles (diagnosis of exclusion, multifactorial encephalopathy workup, neurotoxic drug screening) generalize broadly to critical care neurology and other metabolic encephalopathies, though the paper is disease-specific.
Study Usefulness
70%
Highly useful clinically as a structured diagnostic checklist still reflected in modern guidelines and reviews; its prognostic anchors (EEG grading, GCS) remain educationally valuable despite dated prevalence estimates.
Study Reproducibility
40%
As a narrative review with no systematic search strategy, no inclusion criteria, and no underlying dataset, its synthesis cannot be independently reproduced; reproducibility is limited to verifying the claims of its cited primary studies.
Explanatory Depth
70%
The review offers deep mechanistic layering (vagal/circumventricular signaling, endothelial activation, BBB, neurotransmitters, mitochondria, apoptosis) but stops at correlational/plausibility level—causal chains in humans remain unproven, and it correctly flags this.
We'll email you the results when your analysis is finished.
Hypothesis Graveyard
'SAE is primarily a cerebral perfusion failure'—the review itself cites contradictory human and experimental cerebral blood flow data, and the later Pfister study shifted the field toward autoregulation disturbance, not absolute flow, undermining a pure ischemia model.
'Correcting hyperglycemia with intensive insulin will protect the brain in SAE'—plausible from LPS/oxidative stress data cited in the review, but not confirmed in acute stroke trials, and sepsis alters both BBB insulin permeability and neuronal glucose transporter expression, making the intervention effect unpredictable.

 Explore by Goal
 Quick Explanation
 Long Explanation
 Top Data Sources
 Ask a Follow-Up
 Key Insight
 Keep Exploring
 Hypothesis Graveyard
 Potential Experiments
 Discussion
